How automated veterinary discharge instructions reach owners
By Precipitate · 29 October 2026
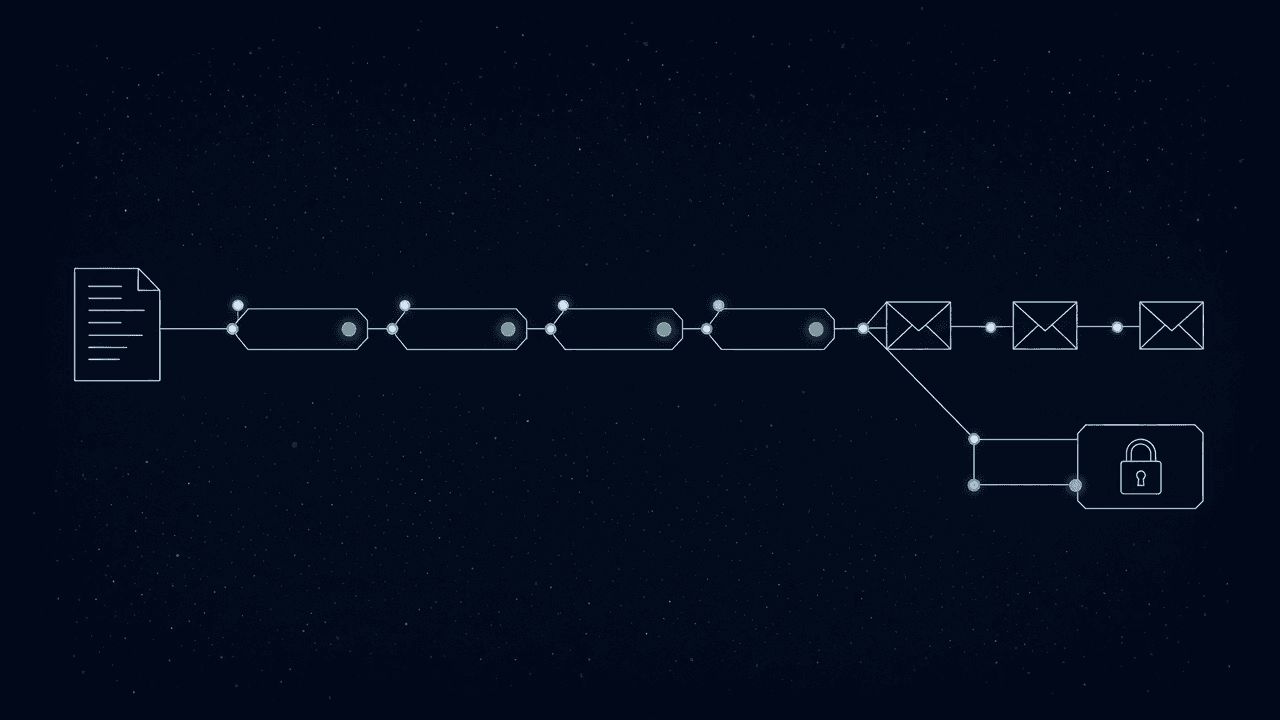
Automated discharge instructions in a veterinary practice should begin with the approved medical record, pass through a clinical review, reach the pet owner through an agreed channel, and record delivery. The useful automation is not the writing step alone. It is the controlled workflow around missing data, approval, delivery failure, owner questions, and follow-up.
The workflow starts before discharge
A reliable workflow starts when the patient enters the specialty or emergency service. The system identifies the referring practice, attending clinician, owner contact details, preferred communication channel, and expected discharge path. It does not wait until the owner is already at reception.
Referral records often arrive through email, uploads, or direct messages. An agent can match each document to the correct patient and check whether the expected material is present. The same intake pattern is covered in our guide to automated referral intake at a vet clinic. Uncertain matches and missing records go to a person rather than into the patient file.
The agent can work around ezyVet, Cornerstone, AVImark, or Instinct, but the connection method matters. Some practices can use supported interfaces. Others may need controlled exports, inbox processing, or staff-approved updates. The practice management system remains the source of record. The agent should not create a second medical history that staff must reconcile later.
The medical record becomes a draft, not a final message
Once the clinician marks the case ready for discharge, the agent reads the approved parts of the record. These may include the diagnosis, procedure, medication orders, feeding instructions, activity restrictions, follow-up plan, and warning signs selected by the clinical team.
The agent then assembles a discharge draft from practice-approved language. It can convert structured medication orders into a readable schedule and place case-specific instructions beside standard care material. Veterinary House publishes separate postoperative sheets for general, dental, soft tissue, and orthopaedic procedures. That source shows why procedure-specific material is more useful than one generic sheet.
The draft should preserve clinical meaning. It should not infer a diagnosis, invent a medication instruction, or fill an empty follow-up date. If a required field is absent, the workflow pauses and asks the assigned clinician or nurse for the missing information. A blank field is safer than a confident guess, but neither should reach the owner.
VETgirl says clear, concise discharge information matters in general, emergency, and specialty practice. The automation should support that standard through plain wording and consistent structure. It cannot decide what medical advice is appropriate for an individual patient.
Clinical checks happen before approval
Before a draft enters the approval queue, deterministic checks can catch common workflow defects. The system can compare the patient name and species with the active encounter, confirm that every medication mentioned has an approved order, and flag conflicting times or duplicate instructions.
These checks are guardrails, not clinical judgment. A veterinarian or authorised team member still approves instructions when the content affects treatment, medication, warning signs, or follow-up care. Practices can define narrower rules for routine documents, but those rules should be explicit and reviewed.
The approval screen should show the source fields beside the generated text. Staff need to see where each instruction came from without searching through the whole record. Any manual edit should be saved with the approver, time, and version. Our article on audit trails for AI agents explains the records an automated system should retain.
Delivery is a tracked workflow
Approval triggers delivery through the owner's agreed channel. The message can include the discharge instructions, medication schedule, follow-up details, and practice contact route. Sensitive documents should use the practice's approved secure method rather than an unprotected attachment when policy requires it.
Sending is not the same as delivery. The agent records whether the message was accepted by the delivery service, rejected, or left without a usable status. A bad email address or failed text message creates a task for staff. The agent can try another approved channel only when the practice has permission and a clear rule for doing so.
The workflow should also account for timing. Instructions may be sent before collection so an owner can read them, then confirmed at handover. Emergency cases may need immediate verbal explanation as well. Automation cannot tell whether an owner understood a complex instruction merely because a message was opened.
If the practice offers translated instructions, the clinical team should approve the terminology and fallback process. Machine translation can help prepare text, but ambiguous medical language needs human review. The original approved instructions should remain attached to the same record.
Owner replies need classification and limits
Replies often contain several kinds of request. An owner may confirm receipt, ask an administrative question, report a symptom, or say that a medication instruction is unclear. The agent can classify the message and route it to the correct queue.
Administrative questions can use approved answers. Medical questions should go to clinical staff. Urgent wording should trigger the practice's escalation rule, not an improvised response from the agent. The system should acknowledge receipt without suggesting that a patient is safe or that treatment can wait.
This is where many simple message automations fail. They send polished instructions but do not manage replies, failed delivery, or unresolved tasks. Our guide to where AI agents fail in real systems covers the need for explicit failure states and human ownership.
Follow-up closes the loop
After delivery, the workflow watches for required actions. It can create a reminder tied to the discharge plan, check whether a follow-up appointment exists, and route an unanswered scheduling task to reception. It can also notify the referring practice after the clinical summary has approval.
Estimate approval belongs in a related but separate workflow. A discharge agent should not treat an unsigned estimate, a payment status, or a clinical consent as interchangeable. Each has its own source record, approval rule, and escalation path.
A useful dashboard shows cases waiting for clinical approval, messages that failed, owner questions awaiting review, and follow-up tasks without an owner. Staff should be able to stop the agent for one case without disabling the whole system. They also need a clear way to correct a record and resend the approved version.
What to measure in your practice this week
Start with a sample of recent discharges. Record when the clinician finished the medical plan, when the owner received instructions, whether staff had to copy information between systems, and which cases required a second message.
Then inspect every exception. Look for missing contact details, incomplete medication orders, drafts waiting without an assigned reviewer, failed messages, and owner replies left in a shared inbox. Those exceptions define the workflow more accurately than the ideal path.
The first automation target should be the repeated handoff with clear source data and clear ownership. Keep clinical judgment with the clinical team. This week, count how many discharges reached the owner with an approved version and a recorded delivery status.
Sources
Want this worked out for your own specialty or emergency veterinary practice?
Get a straight answer →